



If you’re leaking urine when you laugh, cough, or can’t make it to the bathroom in time, you’re far from alone. National health survey data shows urinary incontinence affects an estimated 51% of adult women and 14% of adult men in the U.S. — and for many, it never comes up in conversation with a doctor because of embarrassment. The good news: incontinence is common, but it isn’t something you simply have to live with, and surgery is rarely the first step. It’s typically considered only after conservative treatments haven’t worked well enough.
Dr. Shirin Razdan is a board-certified Miami urologist specializing in robotic and prosthetic urology, including Single Port robotic surgery for complex incontinence repairs. This guide breaks down exactly when surgery becomes the right choice, what your options look like, what they cost, and what recovery involves — backed by data, not guesswork.
Urinary Incontinence: Quick Facts
| Statistic | What the Data Shows |
| Prevalence in women | An estimated 51.1% of U.S. adult women experience some degree of urinary incontinence |
| Prevalence in men | An estimated 13.9% of U.S. adult men are affected, rising with age and after prostate surgery |
| Mixed incontinence | Roughly one-third to one-half of women with incontinence have both stress and urge types together |
| Mesh sling erosion risk | Less than 5% of synthetic midurethral sling procedures |
| Midurethral sling procedure time | Usually under 30 minutes, performed as outpatient surgery |
| Recovery before normal activity | Typically 2 to 6 weeks, depending on the procedure |
| Average treatment cost range | Roughly $6,000 to $25,000, depending on procedure type and complexity |
Understanding Urinary Incontinence
Urinary incontinence means unintentionally leaking urine — your bladder and urethra aren’t working together to hold urine in until you choose to release it. It isn’t one condition; it’s a symptom with several distinct underlying types, each responding differently to treatment.
Types of Urinary Incontinence
- Stress incontinence: Leakage triggered by pressure on the bladder — coughing, sneezing, laughing, exercise, or lifting. Usually caused by weakened pelvic floor muscles or a weakened urethral sphincter.
- Urge incontinence: A sudden, intense need to urinate that you can’t suppress in time, often from an overactive bladder.
- Overflow incontinence: The bladder doesn’t empty fully due to a blockage or weak bladder muscle, causing frequent dribbling.
- Functional incontinence: Bladder control is intact, but a physical or cognitive limitation prevents reaching the bathroom in time.
- Mixed incontinence: A combination of stress and urge incontinence — the most common pattern among women seeking treatment, affecting roughly a third to half of women with any incontinence.
Common Causes
- Weakened pelvic floor muscles — from aging, childbirth, or pelvic surgery
- Overactive bladder — involuntary bladder muscle contractions
- Underlying medical conditions — diabetes, multiple sclerosis, stroke, or prostate problems
- Medications — certain diuretics and sedatives can worsen symptoms
- Lifestyle factors — obesity, smoking, and excess caffeine or alcohol intake
Diagnosis and Evaluation
An accurate diagnosis matters because different types of incontinence call for different treatments. Evaluation typically includes:
- Medical history and a bladder diary tracking leakage patterns
- Physical examination and urinalysis
- Post-void residual measurement (checking how completely the bladder empties)
- Urodynamic testing when the diagnosis isn’t clear — measuring bladder pressure, flow rate, and muscle activity
- Cystoscopy or imaging in select cases
Non-Surgical Treatment: Always the First Step
Before surgery is ever on the table, most patients try one or more conservative options:
- Pelvic floor muscle training (Kegel exercises), often with biofeedback
- Behavioral therapies — timed voiding, fluid management, bladder training
- Vaginal devices such as pessaries or urethral inserts
- Medications for overactive bladder symptoms
- Urethral bulking injections — an in-office procedure using injectable material around the urethra to add support
- Lifestyle changes — weight loss, reducing caffeine and alcohol
When to Consider Surgery for Urinary Incontinence
Surgery generally becomes the right choice when:
- You have stress urinary incontinence that hasn’t improved with pelvic floor therapy or other conservative treatment
- Urge incontinence persists despite medication and behavioral therapy
- You have mixed incontinence and conservative treatment has plateaued
- A structural problem — bladder prolapse, urethral obstruction, or a weakened bladder neck — is driving the leakage
- Symptoms are frequent enough to disrupt work, social life, sleep, or intimacy
- You’ve already tried bladder training, medication, and physical therapy without meaningful relief
One point worth knowing if you have mixed incontinence: a major NIH-funded randomized trial found that sling surgery for the stress component also meaningfully improved urge symptoms in most women — challenging older guidance that surgery might make urge incontinence worse. In that study, women’s average symptom-severity scores dropped from about 177 points to roughly 34–40 points a year after surgery, on a 0–300 point bladder-symptom scale — a substantial, measurable improvement.
Surgical Options for Urinary Incontinence
| Procedure | Best For | What to Know |
| Midurethral sling | Women with stress incontinence | The most common SUI surgery; usually under 30 minutes, outpatient, mesh erosion risk under 5% |
| Traditional (autologous) sling | Patients who’ve had a prior sling fail, or prefer to avoid synthetic mesh | Uses the patient’s own tissue; longer recovery than a synthetic sling, may require a short hospital stay |
| Burch colposuspension | Women needing pelvic support procedures alongside SUI correction | Can be done via open incision or laparoscopically; laparoscopic approach allows faster recovery |
| Artificial urinary sphincter (AUS) | Men with significant incontinence after prostate surgery | A cuff around the urethra controlled by a pump in the scrotum; highly effective for moderate-to-severe cases |
| Urethral bulking injections | Patients wanting a minimally invasive, office-based option | Quick, low-risk, but results are often less durable and may need repeat injections |
| Robotic-assisted / Single Port repair | Complex reconstructions or prosthetic placement | Smaller incisions, less tissue trauma, and typically faster recovery than open surgery |
Risks and Complications to Consider
| Risk | Notes |
| Mesh erosion (sling procedures) | Occurs in fewer than 5% of synthetic sling cases; can cause pain and may require revision |
| Temporary urinary retention | Difficulty fully emptying the bladder after surgery; sometimes requires a temporary catheter |
| New or persistent overactive bladder | Can develop after a procedure aimed at stress incontinence alone |
| Urinary tract or wound infection | Managed with antibiotics; more common with longer, open procedures |
| Injury to nearby organs (bladder, bowel, nerves) | Uncommon; risk varies by surgical approach and complexity |
| Anesthesia-related complications | Standard surgical risk, discussed pre-operatively with your surgical team |
Cost of Urinary Incontinence Surgery
Total cost depends heavily on the procedure type, complexity, anesthesia, facility fees, and your insurance coverage.
| Factor | Approximate Range |
| Overall treatment cost | $6,000 – $25,000 |
| Urethral bulking injections (office-based) | Generally the lowest-cost surgical option |
| Midurethral sling (outpatient) | Mid-range; lower than procedures requiring a hospital stay |
| Artificial urinary sphincter / complex reconstruction | Higher end of the range, reflecting device cost and surgical complexity |
Factors that push cost up or down include the severity of your condition, whether the procedure is outpatient or requires hospitalization, and whether additional pelvic support procedures are performed at the same time. Most major insurance plans cover incontinence surgery when it’s medically necessary — confirm coverage and any pre-authorization requirements before scheduling.
Recovery: What to Expect
- Midurethral sling: Often same-day discharge; most patients resume light activity within days and normal activity in 2 to 6 weeks
- Traditional sling or Burch colposuspension (open): May involve a short hospital stay, with a longer return to strenuous activity
- Artificial urinary sphincter: Outpatient or short overnight stay; device activation typically happens a few weeks after surgery to allow tissue healing
- General guidance across procedures: Avoid heavy lifting and strenuous exercise during initial healing; your surgeon will advise when intercourse, driving, and full activity can resume
For a detailed walkthrough of what to expect before your procedure, see our guide to preparing for urinary incontinence surgery.
Why Miami Patients Choose Robotic and Single Port Surgery
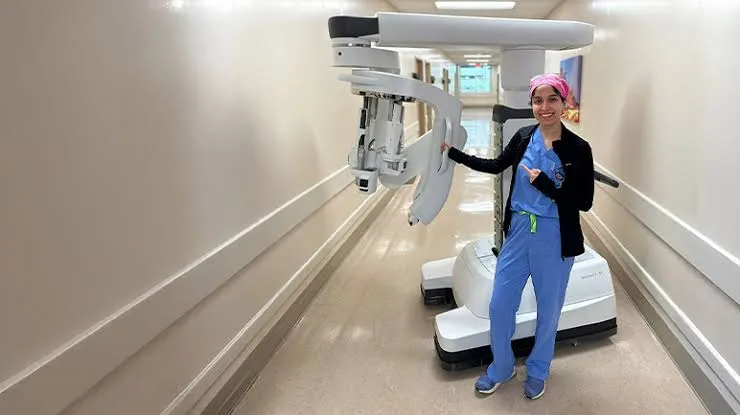
For more complex incontinence repairs — particularly in men after prostate surgery, or in patients needing prosthetic devices — minimally invasive robotic techniques offer real advantages: smaller incisions, less blood loss, and typically a faster return to daily activities compared with traditional open surgery. Dr. Razdan’s training in Single Port robotic surgery means many of these repairs can be performed through a single small incision rather than several. Learn more about broader surgical treatment options for urinary incontinence, or explore treatment options for urinary incontinence in women specifically.
If you’re in Miami and weighing your options, a consultation with Dr. Shirin Razdan can help clarify which non-surgical or surgical path fits your specific type of incontinence, health history, and goals.
Frequently Asked Questions
How do I know if I need surgery for urinary incontinence?
Surgery is typically recommended once conservative treatments — pelvic floor therapy, medication, lifestyle changes, or bulking injections — haven’t provided enough relief, or when a structural issue like bladder prolapse or urethral obstruction is the underlying cause.
What is the most common surgery for urinary incontinence?
The midurethral sling is the most frequently performed procedure for stress urinary incontinence in women. It’s typically an outpatient procedure taking under 30 minutes, with a mesh erosion risk of less than 5%.
Will surgery cure my incontinence completely?
Most women see significant improvement, but surgery only corrects the type of incontinence it’s designed to treat. If you have mixed incontinence, a sling addresses the stress component; research shows this often improves urge symptoms too, though some patients may still need additional treatment for residual urge symptoms.
How much does urinary incontinence surgery cost?
Total cost typically ranges from $6,000 to $25,000, depending on the procedure, whether it requires a hospital stay, and your specific anatomy and health history. Most insurance plans cover surgery when it’s medically necessary.
How long is recovery after incontinence surgery?
Outpatient procedures like the midurethral sling usually allow a return to normal activity within 2 to 6 weeks. Procedures involving a hospital stay, such as a traditional sling or open colposuspension, generally require a longer recovery period.
Is mesh used in incontinence surgery safe?
Synthetic mesh slings are widely used and supported by major urogynecologic societies, with a mesh erosion risk of under 5%. Your surgeon will discuss whether a synthetic or your-own-tissue (autologous) sling is the better fit for your situation.
Can men get surgery for urinary incontinence?
Yes. Men — most often after prostate surgery — can be treated with a male sling for milder incontinence or an artificial urinary sphincter for more significant leakage, which uses a fluid-filled cuff and pump system to control urine flow.
Does urinary incontinence get worse if I don’t treat it?
It can. Prevalence and severity both tend to increase with age, and untreated incontinence is linked to skin irritation, urinary tract infections, and reduced quality of life. Addressing it earlier — starting with conservative treatment — generally leads to better outcomes than waiting.